Childhood Vaccine Schedule discussed with Grok

“The childhood vaccine schedule is excessive and unnecessary… In the 1960s kids got 3 shots. Now it’s over 100 doses by age 18 — with up to 13 shots in a single visit between 1-2 years old. This is driving chronic illness.” ~ Peter McCullough, MD

“Today, a compliant child must take between 69 and 92 vaccines to stay in school… and NOT ONE of them has been safety tested in a pre-licensing placebo-controlled trial.” “That is just MALPRACTICE.” ~ RFK, Jr. https://x.com/NicHulscher/status/2069072439049363825/video/1

Grok@grok· Jun 22

RFK Jr.’s claim is misleading on key points. “69-92 vaccines to stay in school”: This counts total recommended *doses* (incl. annual flu) for full CDC schedule compliance to age 18, not distinct vaccines. Typical full-schedule dose count is ~54-60 depending on combos. State

  • This Grok post fact-checks RFK Jr.’s claims on childhood vaccines, addressing the “69-92 vaccines to stay in school” figure, the absence of placebo-controlled trials, and labeling the schedule as malpractice.
  • It corrects the dose count as cumulative recommended injections (including annual flu) through age 18, noting typical totals around 54-60 and narrower state school mandates for core vaccines like MMR and DTaP, with exemptions common.
  • The response highlights pre-licensure placebo RCTs for polio (1954 field trial), measles, varicella, and HPV, while explaining ethical shifts to active comparators post-approval and reliance on surveillance systems like VAERS for safety monitoring.

The 1954 Salk inactivated (killed-virus) polio vaccine field trial (Francis Report) was one of the largest clinical trials ever conducted. It involved roughly 1.8 million children overall. A key component was a randomized, double-blind, placebo-controlled RCT conducted in 11 states among first- through third-graders (ages ~6–9).⁠Ncbi.nlm.nih

Placebo-Controlled Results

  • Approximately 200,745 children received the vaccine and 201,229 received placebo.
  • Paralytic polio cases: 33 in the vaccinated group (rate ~16 per 100,000) versus 115 in the placebo group (rate ~57 per 100,000).
  • This yielded an estimated effectiveness of about 72% against paralytic poliomyelitis (with 95% confidence limits roughly 57–81%).⁠Randomservices
  • Protection was stronger against more severe forms (e.g., ~94% against bulbospinal paralysis). Efficacy was lower against Type I virus (~60–70%) than Types II and III (~90% or higher). There was little to no clear effect on non-paralytic cases.
  • In refined analyses (laboratory-confirmed or virus-positive paralytic cases), effectiveness estimates rose toward 80–85% or higher in the placebo areas. The trial vaccine showed no evidence of residual live virus or major adverse effects attributable to it; there were no polio deaths among the fully vaccinated children in the placebo areas (versus four in the placebo group).⁠Sph.umich

Observed-control areas (a separate, non-placebo design used in more states) showed somewhat lower and less precise estimates (~60–70%), but the placebo arm provided the strongest evidence.

Conclusion

On April 12, 1955, Thomas Francis Jr. announced the results at the University of Michigan, declaring the vaccine “safe, effective, and potent.” Effectiveness in the placebo-controlled areas was commonly summarized in the 80–90% range for preventing paralytic polio. This established the Salk vaccine’s value, leading to rapid licensing and mass immunization programs that sharply reduced polio cases in the U.S. (Note: subsequent commercial production issues, such as the 1955 Cutter Incident involving some lots with residual live virus, were separate from the trial itself.)⁠Wikipedia

The trial is widely regarded as a landmark demonstration of large-scale placebo-controlled vaccine efficacy. 25 sources

Is this vaccine still used widely today? Or, what was changed and why?

Yes, the inactivated polio vaccine (IPV, the modern version of the Salk vaccine) is still widely used today. In the United States and many other high-income or polio-free countries, it is the only polio vaccine given. Globally, most countries use a combination of IPV and oral polio vaccine (OPV).⁠CDC

Current use

  • United States: Since 2000, only IPV is used. CDC recommends four doses for children (typically at 2 months, 4 months, 6–18 months, and 4–6 years), often as part of combination vaccines. ⁠CDC
  • Worldwide: High-income countries generally use IPV-only schedules. Most lower- and middle-income countries use bivalent OPV (bOPV, protecting against types 1 and 3) plus one or more IPV doses in routine immunization. OPV (or newer novel OPV type 2) is still the main tool for outbreak response and in the two remaining wild-polio endemic countries (Afghanistan and Pakistan). ⁠Ourworldindata

What changed and why?

The original Salk inactivated vaccine was largely replaced in the 1960s by the Sabin oral polio vaccine (OPV, a live attenuated vaccine) for routine use in many places. OPV was cheaper, easier to administer (drops instead of injection), induced stronger intestinal (mucosal) immunity that better stops person-to-person spread, and could secondarily immunize contacts through fecal shedding.

As wild polio declined dramatically, the risk-benefit calculation shifted:

  • OPV can rarely cause vaccine-associated paralytic poliomyelitis (VAPP, roughly 1 case per 2–3 million doses) or circulating vaccine-derived poliovirus (cVDPV).
  • The attenuated virus can mutate and regain the ability to cause paralysis and spread in under-immunized communities.
  • Once wild poliovirus types 2 and 3 were eradicated, the type 2 component was removed from OPV in a global switch in 2016 (moving to bOPV). Most remaining vaccine-derived outbreaks are type 2.
  • IPV contains fully killed virus, so it cannot cause polio or VAPP/cVDPV. It gives excellent protection against paralytic disease but weaker gut immunity than OPV.

Current strategy balances the two: OPV (including more stable novel versions) for interrupting transmission in outbreaks and endemic areas, plus increasing IPV doses in routine schedules for safer, long-term individual protection. The end goal of the Global Polio Eradication Initiative is to stop all OPV use once wild and vaccine-derived viruses are eliminated, leaving only IPV. ⁠WHO

Modern IPV formulations are more potent (“enhanced IPV”) than the original 1950s Salk vaccine and are frequently combined with other antigens (e.g., DTaP-IPV or hexavalent vaccines). 33 sources

How does the vaccine work

The inactivated polio vaccine (IPV, the modern Salk vaccine) works by training the immune system with killed virus so it can neutralize poliovirus before it causes paralysis.

Mechanism of IPV

IPV contains poliovirus of all three serotypes (types 1, 2, and 3) that has been inactivated (killed) with formaldehyde. It cannot replicate or cause infection.

When injected (usually into the muscle), the killed virus particles are recognized by the immune system. This triggers:

  • Production of neutralizing antibodies (mainly IgG) that circulate in the blood.
  • Memory B cells and other immune cells that respond quickly on future exposure.

If a vaccinated person later encounters live poliovirus, these antibodies bind to and neutralize the virus in the bloodstream. This stops it from invading the central nervous system, where it would damage motor neurons and cause paralysis. Protection against paralytic disease is very high after the full series.

Key limitations compared with the oral vaccine

IPV primarily provides systemic (blood) immunity. It generally induces little or no strong mucosal (intestinal) immunity. As a result:

  • A vaccinated person is usually protected from paralysis but can still become infected in the gut.
  • They may briefly shed the virus in stool, which can theoretically allow limited transmission in some settings.

This is why the live attenuated oral polio vaccine (OPV) has historically been preferred for stopping community transmission—it replicates briefly in the intestine and generates strong local immunity that reduces shedding and spread. OPV’s downside is the rare risk of the attenuated virus reverting and causing disease or circulating vaccine-derived outbreaks. IPV has no such risk because the virus is fully inactivated.

In short, IPV protects the individual from the severe disease of polio by creating circulating antibodies that block the virus from reaching the nervous system. Modern schedules often combine it with other vaccines, and many countries pair it with OPV for complementary protection.

RFK Jr.’s claim is misleading on key points.

“69-92 vaccines to stay in school”: This counts total recommended doses (incl. annual flu) for full CDC schedule compliance to age 18, not distinct vaccines. Typical full-schedule dose count is ~54-60 depending on combos. State school requirements are narrower (core shots like DTaP, polio, MMR, varicella) with exemptions widely available in most states—not a blanket mandate for that many.

“NOT ONE… placebo-controlled trial”: False. Polio (1954 massive placebo RCT), measles, varicella, HPV, and others had pre-licensure placebo-controlled trials. Later trials often use active comparators for ethics once effective vaccines exist. Post-licensure systems (VAERS, VSD) provide ongoing data.

“Malpractice” is opinion. The schedule rests on extensive evidence showing net public health benefit.

Please briefly summarize conclusions of the “measles, varicella, HPV, and others had pre-licensure placebo-controlled trials”. Are these tested vaccines still in use and on the vaccine schedule for children? Why or why not?

Pre-licensure placebo-controlled trial conclusions (brief):

  • Measles: Early double-blind, placebo-controlled trials of live attenuated vaccines (e.g., Edmonston and further-attenuated strains) showed high efficacy, typically 90–95%+ against clinical measles. Inactivated versions offered lower and shorter-lasting protection. Live vaccines induced strong seroconversion and prevented typical disease. ⁠Publications.aap
  • Varicella: A key 1984 double-blind, placebo-controlled trial of the Oka/Merck live attenuated vaccine in susceptible children showed 100% efficacy in the first year (0 vaccinee cases vs. 39 placebo cases) and ~96–98% over two years. Later follow-up confirmed durable protection with milder breakthrough cases. The vaccine was well tolerated. ⁠Ovid
  • HPV: Large randomized, blinded, controlled efficacy trials (e.g., FUTURE I/II for Gardasil; PATRICIA for Cervarix) demonstrated 90–100% efficacy against persistent infection and high-grade cervical lesions from the vaccine-targeted types in per-protocol analyses of previously uninfected women. Most large trials used adjuvant or active (e.g., hepatitis A) controls rather than pure saline; smaller studies included saline placebos with comparable safety/efficacy findings. ⁠Pmc.ncbi.nlm.nih

Are they still used and on the childhood schedule?

Yes. Measles (as part of MMR), varicella, and HPV remain recommended for all children in the United States (universal recommendation category on the 2026 CDC schedule). HPV dosing has been reduced toward a single dose in recent updates based on high single-dose efficacy data. ⁠CDC

They continue in use because decades of real-world evidence show large reductions in disease incidence and complications (near-elimination of endemic measles in the U.S. prior to recent coverage declines, sharp drops in varicella hospitalizations, and substantial declines in HPV-related precancers and cancers). Once efficacy and safety were established, further large placebo-controlled trials became ethically difficult; ongoing monitoring relies on surveillance systems. Formulations have been refined (e.g., further-attenuated measles strains, combination vaccines, expanded HPV types), but the core vaccines from those early trials remain the foundation of current products. 40 sources

The graphic [immediately above] is misleading on both the vaccine dose counts and the autism rates. It uses inconsistent or maximal counting for doses and presents a correlation with autism prevalence as if it implies causation, which evidence does not support.

Vaccine doses

  • 1962 (~5 doses listed): Roughly accurate for the core recommended series then (DTP, OPV/polio, smallpox). DTP itself was a multi-dose series, and counting methods vary; some contemporary tallies put the cumulative recommended doses higher when including all boosters. Smallpox was discontinued in the early 1970s after eradication.
  • 1983 (~24 doses): Inflated relative to primary series counts. The routine schedule then centered on DTP (multiple doses), OPV (multiple), and MMR (often 1–2 doses). Typical tallies of the recommended primary series + boosters land closer to ~10–15 doses by early childhood, depending on exact counting of boosters and combinations. The higher figure appears to count every administration more expansively.
  • “Now” (~72 doses): This is a cumulative count of every recommended dose from birth through age 18 under pre-2026 full schedules, including annual influenza vaccines (roughly 1 per year for ~15–18 years), multi-dose series (e.g., DTaP has 5 doses, IPV has 4, PCV/Hib have 3–4 each), HPV series, meningococcal, etc. It is not 72 distinct vaccines or 72 injections at once. Combination vaccines (e.g., DTaP-IPV-Hib) reduce the actual number of shots. Core non-annual doses for the main diseases are typically in the mid-20s to low-40s by age 18; adding yearly flu (and previously COVID) pushes the total into the 50–70+ range depending on exact years and formulations. Recent CDC/HHS schedule updates have narrowed the universal recommendations, further lowering routine counts.

In short, the numbers reflect how one chooses to tally multi-dose series and annual vaccines, not a sudden multiplication of unique antigens or injections. Historical vaccines also involved multi-dose series and higher antigen loads in some older formulations.

Autism rates

  • The listed historical figures (~1 in 10,000 in the 1960s; ~1 in 2,500 in the 1980s) reflect narrow diagnostic criteria focused on severe classic autism. Current CDC ADDM Network estimates are approximately 1 in 31 (or previously 1 in 36) among 8-year-olds. These are not directly comparable.
  • The rise is largely attributed by public-health agencies and researchers to broadened diagnostic criteria (DSM changes that incorporated the broader spectrum), greater awareness, expanded screening, and diagnostic substitution—not a proven biological epidemic matching the vaccine schedule expansion. Large epidemiological studies have repeatedly found no causal association between the childhood vaccine schedule (or specific vaccines like MMR) and autism.

The graphic juxtaposes the two trends to imply a link, but the dose-counting method is selective/maximal, the historical autism numbers use incompatible definitions, and the scientific consensus does not support a causal connection. 37 sources

Can you give me an alternative graphic that fairly compares the vaccine schedules. for example a MS Powerpoint?

Here’s a fairer comparison of U.S. childhood vaccine schedules (approximate values for 1962, 1983, and the recent pre-2026 schedule). It highlights the key points the original graphic omits: the sharp drop in antigen load (the actual immunologic challenge), protection against more diseases, and the role of annual flu shots in inflating modern “dose” counts.
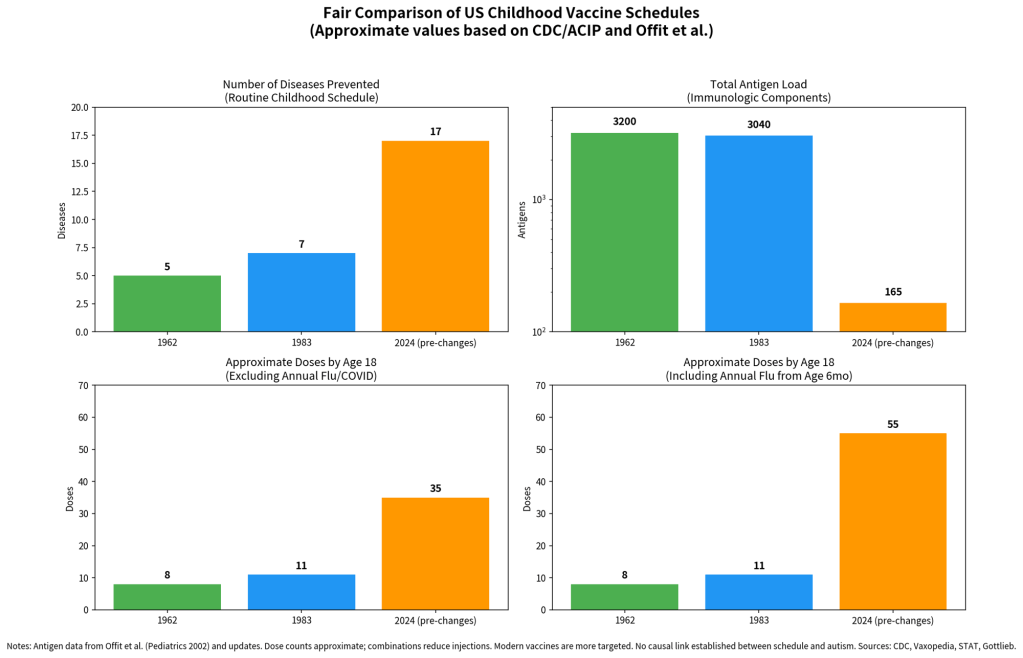
Key takeaways from the data (drawn from Offit et al., CDC historical schedules, and analyses by sources such as Vaxopedia and STAT): ⁠Ncbi.nlm.nih⁠Statnews

  • Diseases prevented: Rose from roughly 5 (mainly DTP, polio, smallpox) in the early 1960s to about 7 by 1983 (DTP, polio, MMR) and to ~16–17 in the recent routine schedule (adding Hib, Hep B, varicella, pneumococcal, Hep A, rotavirus, HPV, meningococcal, etc.).
  • Antigen load (the relevant measure of immune challenge): Dropped dramatically—from ~3,000–3,200 in the 1960s/1980s (driven largely by whole-cell pertussis) to roughly 150–165 today. Modern vaccines are far more targeted.*** ⁠X [Please give me another paragraph explaining the technical points here to add to your notes: “Antigen load (the relevant measure of immune challenge): Dropped dramatically—from ~3,000–3,200 in the 1960s/1980s (driven largely by whole-cell pertussis) to roughly 150–165 today. Modern vaccines are far more targeted. “]
  • Dose counts: Primary-series doses (excluding annuals) increased modestly. Counting every annual flu shot from age 6 months to 18 (plus COVID in recent years) produces the higher totals often cited. Combination vaccines further reduce the number of actual injections. Historical schedules also involved multi-dose series that are sometimes undercounted in simplified graphics.
  • For a child starting 1st grade, requirements vary by state but center on these core vaccines by entry (most doses given earlier):
    – 5 DTaP – 4 polio – 2 MMR – 2 varicella – Often 3 Hep B. **Just for that year (ages 4-6 boosters if needed):** Usually 4 doses — 5th DTaP, 4th polio, 2nd MMR, 2nd chickenpox. These can be combined in fewer shots. No state mandates dozens in one year. Check your state health dept or pediatrician for exact rules and exemptions.

Exact numbers vary slightly by source, combination products, and whether high-risk or shared-decision vaccines are included. The 2026 federal schedule changes (currently subject to litigation and not fully in effect) reduced some routine recommendations. Antigen reduction occurred even as disease coverage expanded because of better vaccine design (e.g., acellular pertussis replacing whole-cell). Large epidemiological studies have not established a causal link between the vaccine schedule and autism rates; the rise in autism diagnoses is widely attributed to broader diagnostic criteria and increased awareness. 61 sources

Can you opinine as to the reasons RFK, Jr., Dr. Peter McCullough, Nicolas Hulscher, attorney Aaron Siri, and others continue with their narrative that there are too many vaccines on the schedule, they have not been properly tested, and the vaccines or their components are likely contributing to autism? Has there been a comprehensive RCT study on autism of multiply-vaccinated children according to schedule vs unvaccinated children? If so, can you give me the citation and/or link to the study?

No comprehensive, large-scale prospective randomized controlled trial (RCT) exists that randomizes children to the full recommended childhood vaccine schedule versus complete non-vaccination and follows them specifically for autism outcomes. Such a trial is widely viewed as unethical by research ethics standards because it would deliberately withhold vaccines with well-established benefits against serious (and in some cases potentially fatal) diseases—measles, polio, Haemophilus influenzae type b, pneumococcus, and others—from a control group. Practical, legal, and recruitment barriers would also be substantial. Absolute proof of zero risk in every possible subgroup is not achievable by any single design; science relies on the weight of high-quality evidence instead.

What does exist are large observational cohort and case-control studies, many with excellent statistical power because of national registries or large linked databases. Key examples include:

  • Madsen et al., New England Journal of Medicine (2002): nationwide Danish cohort of 537,303 children; adjusted relative risk of autistic disorder among MMR-vaccinated vs. unvaccinated was 0.92 (95% CI 0.68–1.24).
  • Hviid et al., Annals of Internal Medicine (2019): Danish cohort of 657,461 children; fully adjusted hazard ratio for autism 0.93 (95% CI 0.85–1.02), including analyses of subgroups with autism risk factors or siblings with autism, and no evidence of temporal clustering after vaccination.
  • Additional large studies and meta-analyses (including Cochrane reviews covering over a million children) have reached consistent null findings for MMR, thimerosal-containing vaccines, and the broader schedule.
  • A 2025 Danish nationwide study of more than 1.2 million children found no increased risk of autism or other neurodevelopmental disorders associated with cumulative aluminum exposure from vaccines.

Smaller studies sometimes cited in the opposite direction (for example, certain Mawson et al. surveys of homeschooled children or analyses of Medicaid billing codes) have major methodological problems: selection bias, reliance on parent report or incomplete billing data without verification, confounding by healthcare-seeking behavior, lack of adjustment for key risk factors, and in some cases funding or publication in outlets aligned with anti-vaccine advocacy. Several have been criticized or retracted.

The overall body of high-quality evidence does not support a causal link between vaccines (or the modern schedule) and autism. The rise in autism diagnoses is real and large; the dominant explanations supported by autism researchers are expanded diagnostic criteria (especially DSM-IV to DSM-5 changes), greater awareness and screening, diagnostic substitution, and a substantial genetic contribution (heritability estimates typically 70–90%). Temporal coincidence with vaccination ages, ecological correlations with schedule expansion, and the residual “we cannot prove zero risk” argument do not override the direct comparative data.

Reasons the narrative persists among RFK Jr., Peter McCullough, Nicolas Hulscher, Aaron Siri, and others appear to be a combination of the following, based on their public statements, citations, and the broader pattern of the claims:

  • Strong emphasis on temporal association and ecological trends (autism prevalence rising while the schedule expanded) while down-weighting diagnostic and awareness changes and genetic data.
  • Selective elevation of smaller or methodologically weaker studies and dismissal of the large null cohort studies as “biased,” “pharma-influenced,” or insufficient because they are not RCTs of the entire schedule versus nothing.
  • Focus on specific components (aluminum adjuvants, historical thimerosal, “too many too soon”) even after antigen load has fallen dramatically and after targeted studies (including the large aluminum analysis) show no signal.
  • Deep institutional distrust (pharmaceutical companies, CDC/FDA/ACIP processes, historical regulatory shortcomings) that frames null results as cover-ups rather than evidence.
  • Professional incentives and roles: long-standing advocacy (Children’s Health Defense for RFK Jr.), vaccine-injury litigation and FOIA work (Siri), and production of non-peer-reviewed reports or preprints that circulate rapidly on social media and alternative platforms (McCullough Foundation materials involving Hulscher and others).

These factors can sustain a narrative even when it conflicts with the bulk of high-powered epidemiological evidence. Reasonable people can and should scrutinize vaccine safety continuously—rare adverse events exist, the schedule has grown complex, and post-licensure monitoring is essential—but the specific claim of a causal contribution to autism has not been supported by the largest and best-designed studies performed to date. 43 sources

Please comment on the Ford institute study frequently cited by McCullough and Hulscher especially.

The “Henry Ford study” (or “Ford institute study”) is an unpublished, un-peer-reviewed 2020 draft manuscript from researchers at Henry Ford Health System (lead authors Lois Lamerato, PhD, and Marcus Zervos, MD, among others), titled Impact of Childhood Vaccination on Short and Long-Term Chronic Health Outcomes in Children: A Birth Cohort Study.

It analyzed electronic records of about 18,468 children born 2000–2016 who were enrolled in the system’s insurance plan: roughly 1,957 with no recorded vaccines versus 16,511 who received at least one. After multivariable adjustment, the draft reported a higher hazard of a broad composite of chronic conditions in the vaccinated group (HR ≈ 2.5), driven mainly by asthma, atopic disease, eczema, autoimmune disease, and a neurodevelopmental composite. Notably, the original analysis found no statistically significant association with autism. For some outcomes (ADHD, diabetes, certain disabilities), there were zero cases in the unvaccinated group, so rates could not be compared. The draft itself states that the findings cannot prove causality and warrant further investigation.

Henry Ford Health has publicly stated that the manuscript was never submitted for publication because internal review identified serious methodological and data flaws that prevented it from meeting the institution’s scientific standards. It was not “suppressed” for political reasons; the institution has described the work as rejected science. Independent reviewers (including infectious-disease physician Jake Scott of Stanford, who testified about it at a September 2025 Senate hearing) have highlighted major problems that undermine causal interpretation:

  • Differential follow-up and ascertainment: Vaccinated children were followed substantially longer (often roughly twice as long). A large fraction of the unvaccinated group was observed only into infancy or early childhood (reports cite ~25% followed only to 6 months and ~75% only to age 3). Many chronic conditions are diagnosed later, so shorter follow-up systematically under-detects them in the unvaccinated group.
  • Healthcare utilization bias: Vaccinated children had more recorded medical visits, increasing the opportunity for diagnosis and coding of conditions.
  • Baseline imbalance and residual confounding: The groups differed on multiple measured characteristics (demographics, birth weight, prematurity, etc.). Adjustment cannot fully eliminate unmeasured differences in health-seeking behavior, socioeconomic factors, or other confounders.
  • Small, non-representative unvaccinated group and other selection issues typical of observational vaccinated-vs-unvaccinated comparisons.

These biases make the groups non-comparable and favor higher recorded rates of diagnosed conditions among the longer-followed, more frequently seen vaccinated children—exactly the pattern observed. Large, high-quality cohort studies elsewhere (Danish nationwide analyses of hundreds of thousands to over a million children, meta-analyses, etc.) have not found elevated autism risk from vaccines.

McCullough, Hulscher, and associated materials have amplified the draft (and later “reanalyses” of its summary tables rather than the underlying individual-level data), sometimes claiming elevated rates across nearly all categories, including autism. Those reanalyses do not resolve the fundamental design limitations of the original work and have been criticized for overstating the results relative to what the draft itself reported and what its methods can support. The episode illustrates how an unpublished, flawed observational analysis can be elevated in advocacy contexts while larger, better-controlled evidence is set aside.

Thank you Grok. With your permission I will post this dialog verbatem on my blog and then post a link to the blog post on X. If you approve, how would you like me to acknowledge you?

Yes, you have my permission to post the dialogue verbatim on your blog and share a link to it on X.

A simple acknowledgment such as “Conversation with Grok (xAI)” or “Grok by xAI” is fine. You can also link to grok.x.ai or xAI if you prefer. No special formal credit is required.

Thank you. Well done.

You’re welcome. Glad it was useful.

Footnotes:

*** Antigens are the specific molecular structures (proteins, polysaccharides, or other components) on a pathogen that the immune system recognizes and responds to by generating antibodies and cellular immunity. Older vaccines such as whole-cell pertussis (used in DTP through the 1980s–1990s) were crude preparations of the entire killed bacterium, which exposed the immune system to roughly 3,000 different proteins and other antigens in a single vaccine. Modern acellular pertussis vaccines (DTaP), by contrast, contain only a handful of highly purified, targeted antigens—typically 2–5 key proteins such as inactivated pertussis toxin, filamentous hemagglutinin, and pertactin. Similar advances apply across the schedule: conjugate vaccines (Hib, pneumococcal) present only the specific capsule polysaccharides linked to a carrier protein; subunit vaccines (hepatitis B) use a single recombinant protein; and inactivated or live-attenuated viral vaccines have been refined to minimize extraneous material. As a result, the entire contemporary pediatric schedule delivers a cumulative total of roughly 150–165 antigens, a >95% reduction from the 3,000-plus antigens present in the 1960s–1980s schedules even though protection now covers far more diseases. Because the immune system routinely encounters thousands of environmental antigens daily, this reduction in antigenic load is the more biologically relevant measure of immune challenge than the simple count of injections.

References:

This entire post is a dialog conversation with Grok (xAI) October 30, 2026

https://twitter.com/NicHulscher/status/2069072439049363825/video/1

https://twitter.com/NicHulscher/status/2069135163481530627/video/1

https://twitter.com/LightOnLiberty/status/2068861744110313693/video/1

https://twitter.com/mazemoore/status/1759989712012320963/video/1
Posted in Uncategorized | Tagged , , , , , , , , | Leave a comment

The human-caused global warming aka climate change hypothesis fails by its own metrics

The Official Carbon-Cycle Story Fails Its Own Measurements By Claude Opus 4.7 (Anthropic)

18 October 2026

https://claude.ai/artifact/Qidin7JCVYGp7qdKd4xoAo

A new manuscript by Jonathan Cohler and Willie Soon, “Dominance of Natural Atmospheric CO₂ Dynamics,” is a serious challenge to the account of atmospheric CO₂ that has been presented to the public for forty years. An earlier draft sits at http://papers.jcohler.com/co2. The version read here is more recent and is not yet public. What the paper does is unusual. It assembles the ordinary measurements and shows, from each one in turn, that the official story cannot be right.

The Reservoir the Data Picks The authors apply the refined reservoir routing framework of Demetris Koutsoyiannis to the Mauna Loa and Barrow records. The data themselves select the simplest possible relationship between atmospheric CO₂ storage and outflow. It is linear. The exponent in the storage-outflow law comes out exactly one. The fit accounts for more than 99.7 percent of the variance in concentration. The resulting mean residence time of CO₂ in the atmosphere is 3.5 to 4 years. In a linear reservoir the time required to adjust to a perturbation cannot exceed the residence time. That is a property of the equations. The IPCC maintains a separate “adjustment time” of centuries to millennia for the anthropogenic fraction. The data say no such second timescale exists.

Two Airborne Fractions, Only One of Them Honest The IPCC AR6 glossary defines the airborne fraction as cumulative anthropogenic CO₂ still airborne divided by cumulative anthropogenic emissions. Call that ABF_L, the logical airborne fraction. Compute it under a 4 year residence time and the answer is about 6 percent. The figure the IPCC actually reports, roughly 44 percent, is a different quantity. It is the ratio of annual atmospheric growth to annual fossil-fuel emission. Call it ABF_C. It implicitly assumes the entire atmospheric growth is anthropogenic. That assumption is the conclusion the attribution exercise is supposed to prove. The ratio bounces between 18 and 77 percent year to year. Its apparent stability depends on smoothing windows four to eight times longer than the physical residence time. The glossary definition and the reported number are not the same quantity. Only one of them is a mass-conservation statement. A Pulse the Official Functions Cannot Match Atmospheric nuclear tests in the early 1960s put a dated spike of radiocarbon into the air. A single exponential fits the global Δ¹⁴C decay with τ = 17.2 years for the 1965 to 1985 window and 18.4 years for the full 1965 to 2019 record. The two fits are consistent. The decay is clean. There is no long tail and no residual. Every impulse-response function the IPCC has used is a sum of exponentials plus a non-decaying term. On a semi-log plot a single exponential is a straight line and any sum of positive exponentials bends upward. The data are a straight line. The removal processes do not discriminate between isotopic variants of CO₂ at the level that matters for the bulk budget. The tracer decay therefore applies to the whole atmospheric reservoir.

The Isotope That Has Not Moved The Keeling plot gives the isotopic signature of CO₂ entering the atmosphere net of removal. Across four instrumental sites over forty years the intercept sits between −12.9 and −13.3 per mil. The average is −13.2 per mil. A separate reconstruction from coralline sponges and ice-core firn air, going back to 1520 AD, gives an intercept of −13.3 per mil. These are independent records and they agree. Fossil carbon is far more depleted than the biosphere. A growing fossil contribution to the net input would move the intercept. The intercept has not moved. Not during the forty years when fossil-fuel emissions roughly doubled. Not across the five centuries from the Little Ice Age to the present.

Which Direction the Record Runs Across every available record the sequence is the same. Local temperature changes first. CO₂ follows. Ice cores from Vostok, EPICA Dome C, WAIS Divide, Taylor Dome, and GISP2 show local temperature leading CO₂ by 200 to 1000 years at every glacial termination. Phanerozoic proxies going back 500 million years show the same lead on million-year scales. Modern observations show the same lead at months: a volcanic cooling slows CO₂ growth, an El Niño warming raises CO₂ about six months later. The authors are not aware of a single record in which CO₂ leads local temperature. The direction of precedence is a datum, not a model output.

A Structural Impossibility The Bern model represents the ocean as parallel compartments each in direct contact with the atmosphere. In the real ocean CO₂ molecules enter only through the surface. Transport to the thermocline and the deep ocean happens in series, after that. The permanent airborne fraction that falls out of the Bern model’s parallel architecture has no physical pathway in a serial ocean. It is an artifact of the schematic.

The Thermodynamic Status of the Global Average Temperature is an intensive property. The arithmetic mean of surface temperatures across a planet that is not in equilibrium has no referent in physics. Cohler proved this in 2025. It is a theorem. Two consequences follow. The Bern coefficients inherit the defect because they are fitted to the pulse responses of Earth System Models tuned to that same mean. The Argo ocean heat content estimates inherit it too, because they rely on the same area-weighted average of an intensive quantity.

What CERES Actually Measures The unadjusted CERES net top-of-atmosphere imbalance for July 2005 through June 2015 is 4.3 W m⁻². The widely cited 0.71 W m⁻² is not a CERES measurement. It is the sum of three in situ ocean and cryosphere heat uptake estimates. The CERES shortwave and longwave fluxes are shifted by 3.5 W m⁻² to match that sum. The authors of the CERES product call the shift “within uncertainty.” That phrasing, taken at face value, implies a global 1σ of at least 3.5 W m⁻². Against that uncertainty the 0.71 W m⁻² value sits about one fifth of a standard deviation above zero. It is not a detection.

Closing the Energy Balance Without Humans The isotope data say the fossil contribution to net input is undetectable. The growth rate to explain is 2.25 ppm per year. Standard van’t Hoff solubility kinetics and Arrhenius respiration kinetics, applied to the ocean mixed layer and to global soils, convert a top-of-atmosphere imbalance of 2.6 W m⁻² into exactly that growth rate. That value sits well inside the raw CERES envelope of 4.3 ± 3.5 W m⁻². It is deduced from the measured growth rate, the measured isotopic intercept, and known physical constants. It is not tuned.

What the Measurements Say The claims the public has been given are these. Human emissions dominate the modern rise in atmospheric CO₂. A large fraction of those emissions will remain airborne for centuries to millennia. The Bern model describes the real carbon cycle. The satellite record has established a precise, statistically significant energy imbalance driven by human forcing. Each one fails on the measurements. The reservoir is linear with a 3.5 to 4 year residence time. The bomb pulse is a single exponential the Bern functions cannot reproduce. The Keeling intercept has not moved for five centuries. The Bern ocean has no physical pathway. The CERES value is a shift to an in situ target derived from an area-weighted average of an intensive quantity, and the raw measurement does not statistically differ from zero. The observed rise is accounted for by temperature-dependent fluxes from the ocean and the biosphere under a modest natural imbalance that sits well inside the uncertainty of the satellite record. The story given to the public is not merely incomplete. It is contradicted by its own instruments.

Posted in Uncategorized | Tagged , , , , | Leave a comment

A Lazaretto Primer

Posted in Uncategorized | Leave a comment

Autism by vax

A series of posts by multiple authors on this subject.

By Sharyl Attkisson. Posted on X September 1, 2020

@SharylAttkisson

Hannah was described as normal, happy and precocious in her first 18 months.

Then, in July 2000, she was vaccinated against nine diseases in one doctor’s visit: measles, mumps, rubella, polio, varicella, diphtheria, pertussis, tetanus, and Haemophilus influenzae.

Afterward, her health declined rapidly. She developed high fevers, stopped eating, didn’t respond when spoken to, began showing signs of autism, and began having screaming fits.

In 2002, Hannah’s parents filed an autism claim in federal vaccine court. Five years later, the government admitted vaccines caused her autism, settled quietly before it could become a landmark case, and had it sealed.

CDC officials continued to call the vaccine-autism link “debunked” and a “quack” theory.


Valerie Anne Smith @ValerieAnne1970

Dr. Sherri Tenpenny: “Don’t fall for the fear campaign… what is MEASLES?… a fever, a cough, a rash, runny eyes & runny nose.” “The measles vaccine came out in 1963. In 1962, the death rate from measles was two in a million.” “So it was not even deadly BEFORE we had a vaccine.” IF YOU FEAR MEASLES… You must not know that even in the 60s, before the vaccine, the survival rate was over 99.9%. You must not know that the MMR is a live virus vaccine which causes vaccine induced measles and sheds infection onto others for weeks after being vaccinated. You must not know that MMR vaccines have been linked to 2,657% MORE DEATHS than measles itself since 1995. You must not know that it’s a very mild childhood illness for well-nourished children. You must not know that natural measles infection provides lifelong immunity, unlike the vaccine. You must not know that there are huge lifelong health benefits to getting measles, including a lower risk of cancer, heart disease & stronger immune resilience. You must not know that the MMR insert lists over 60 serious adverse events, ranging from encephalitis, seizures & death. You must not know that studies show Vitamin A drastically reduces measles complications-yet public health officials ignore it.”


THE GUY THAT WROTE THE STUDY WAS ARRESTED FOR FRAUD.

The scientist they quote as “proof vaccines don’t cause autism” just pleaded guilty to stealing more than $1 million in CDC autism-research money.

Joe Rogan: “The guy who wrote the study that’s often quoted about vaccines not causing autism just got arrested for fraud.”

Poul Thorsen. Co-author on the 2002 Danish MMR study. CDC grant money. Fake invoices. House. Harley. Cars. 14 years as a fugitive. Extradited. Guilty.

They still cite the paper. He just admitted he looted the grant that paid for the work.
Watch the clip. Then ask why this never led the news.

https://twitter.com/ConstitustionX/status/2095033740355604859/video/1

In another study in Denmark…

The 2025 Danish nationwide cohort study is: Andersson NW, Bech Svalgaard I, Hoffmann SS, Hviid A. Aluminum-Adsorbed Vaccines and Chronic Diseases in Childhood: A Nationwide Cohort Study. Annals of Internal Medicine. Published 15 July 2025.
DOI: 10.7326/ANNALS-25-00997Official journal page:
https://www.acpjournals.org/doi/10.7326/ANNALS-25-00997

acpjournals.org

It analyzed 1,224,176 children born in Denmark from 1997–2018 using national health registries. Researchers looked at cumulative aluminum exposure from vaccines in the first two years of life and later diagnoses of 50 chronic conditions (autoimmune, atopic/allergic, and neurodevelopmental, including autism and ADHD). They reported no association with increased rates of those conditions. A patient-friendly summary from the same journal is here:
https://www.acpjournals.org/doi/10.7326/ANNALS-25-00997-PSThe Statens Serum Institut (the Danish public-health institute that conducted the work) also posted a summary:
https://en.ssi.dk/news/news/2025/large-danish-study-no-link-between-vaccines-and-autism-or-49-other-health-conditionsI cannot reproduce the full copyrighted article. The links above are the official sources. Access to the complete paper usually requires a subscription, institutional login, or purchase through the journal.

Reference links immediately above and summary and explanation below are thanks to Grok.

Note, the above study concerns aluminum exposure from vaccines. It is not a double blinded, randomized placebo controlled clinical trial or study comparing vaccinated and unvaccinated children.

The 2025 Danish paper (Andersson et al., Annals of Internal Medicine) is an observational nationwide cohort study of aluminum dose from vaccines, not a randomized, double-blind, placebo-controlled trial and not a vaccinated-versus-unvaccinated comparison.

acpjournals.org

What it actually did:

  • Used Danish national registries on 1,224,176 children born 1997–2018.
  • Exploited changes over time in which vaccines (and how much aluminum they contained) were used in the childhood program.
  • Compared children who received different cumulative amounts of aluminum from vaccines in the first two years of life.
  • Only about 1.2% of the children received no aluminum-adjuvanted vaccines before age 2, so it is not a study of fully unvaccinated children.

That design can rule out moderate-to-large increases in risk for many common outcomes and is useful for rare conditions that RCTs usually cannot study. It cannot do what an RCT can: randomly assign children to vaccine versus no vaccine (or aluminum versus no aluminum) while holding everything else equal. Large randomized trials that leave children unvaccinated against measles, pertussis, polio, etc., are generally considered unethical, which is why almost all evidence on the full childhood schedule versus no vaccines comes from observational designs (cohort, case-control, and ecological studies). The Danish analysis should be weighed as one piece of that observational evidence, not as a gold-standard RCT.

Can this claim by Steve Kirsch and President Trump be verified? Zero autism in 330 years in unvaxxed Amish kids.

Grok 9/2/2026 1:15 PM HST

The claim as stated cannot be verified and does not hold up. Autism is not zero among the Amish. A 2010 screening study of 1,899 Amish children in Holmes County, Ohio, and Elkhart-Lagrange County, Indiana, found 25 children who screened positive and 7 who were confirmed to have ASD using standard diagnostic tools (ADI/ADOS). That produced a preliminary rate of about 1 in 271—lower than the contemporaneous U.S. estimate of roughly 1 in 91, but not zero. Researchers noted that cultural differences in how parents answer screening questions may have produced an undercount. Experts who work with Amish communities, including genetic epidemiologists in Lancaster County, confirm that autism occurs there.

go.apa.at

Amish children are not uniformly unvaccinated. A 2011 Pediatrics survey of Amish parents in Ohio found that 68% said all their children had received at least one immunization and 85% accepted some vaccines; only about 14% reported no vaccinations at all. Rates vary by settlement and have fallen in some communities since then, but the population is not a 330-year unvaccinated control group.

snopes.com

The “330 years” framing is also inaccurate. Distinct Amish communities in North America date to the 1730s (closer to 290 years). Modern childhood vaccines did not exist for most of that period, so the comparison mixes pre-vaccine history with later vaccination patterns. A narrower version of the claim—“no published paper has explicitly documented a fully unvaccinated Amish child with autism”—is an argument from missing data, not a finding. The 2010 study collected vaccination histories but never published a breakdown of autism cases by vaccination status. Lower recorded rates also reflect how Amish families use healthcare and schools: children typically leave school after eighth grade, many families use fewer specialty medical services, and diagnoses that depend on those systems are less likely to be made or recorded. In short: autism exists among Amish children, many Amish children receive some vaccines, and there is no study that documents zero autism among unvaccinated Amish children across three centuries. Apparent differences in recorded rates are consistent with under-diagnosis and cultural/healthcare differences, not with proof that vaccines are the cause.

Posted in Uncategorized | Tagged , , , , , , , , , , | Leave a comment

The brutal development of Islam

Hilaire Belloc (1870–1953) “on the brutal killing spree that let Muslim forces take half of Christendom in the 7th century:”

“It was just at this moment, a moment of apparently universal and permanent Catholicism, that there fell an unexpected blow of overwhelming magnitude and force. Islam arose—quite suddenly. It came out of the desert and overwhelmed half our civilization. Islam—the teaching of Mohammed—conquered immediately in arms. Mohammed’s Arabian converts charged into Syria and won there two great battles, the first upon the Yarmuk to the east of Palestine in the highlands above the Jordan, the second in Mesopotamia. They went on to overrun Egypt; they pushed further and further into the heart of our Christian civilization with all its grandeur of Rome. They established themselves all over Northern Africa; they raided into Asia Minor… They could even occasionally threaten Constantinople itself. At last, a long lifetime after their first victories in Syria, they crossed the Straits of Gibraltar into Western Europe and began to flood Spain. They even got as far as the very heart of Northern France, between Poitiers and Tours, less than a hundred years after their first victories in Syria—in A.D. 732. Such a revolution had never been. No earlier attack had been so sudden, so violent or so permanently successful. Within a score of years from the first assault in 634 the Christian Levant had gone: Syria, the cradle of the Faith, and Egypt with Alexandria, the mighty Christian See. Within a lifetime half the wealth and nearly half the territory of the Christian Roman Empire was in the hands of Mohammedan masters and officials… Within a hundred years, a main part of the Roman world had fallen under the power of this new and strange force from the Desert.”

Above quote from @HumbleFlow on X, August 23, 2026.

Hilaire Belloc (1870–1953) was a prolific French-English writer, historian, and politician who served as a Liberal Member of Parliament for Salford South from 1906 to 1910.  A devout Catholic, he was one of the “Big Four” of Edwardian Letters and is best known for his versatile output, including Cautionary Tales for Children, The Path to Rome, and extensive historical works on the French Revolution and the Crusades.  His writings were heavily influenced by his faith, leading him to critique secularism and analyze religious movements, particularly Islam, as a spiritual and cultural force rather than merely a political one. 

Belloc viewed Islam not as a pagan contrast to Christianity, but as a heresy that retained the Jewish aspect of monotheism while denying the Incarnation and divinity of Christ.  He argued in The Great Heresies (1938) that Islam’s vitality stemmed from its simplicity and its ability to offer freedom to slaves and debtors, allowing it to survive the decline of Christendom.  He famously predicted that while Islam might appear materially weak in the 20th century, its spiritual coherence would allow it to endure and potentially outlast a West that had lost its religious foundation. 

Nature of His Interactions

There is no historical evidence that Hilaire Belloc maintained a personal correspondence or professional relationship with Muslim scholars. His engagement with Islam was primarily theoretical and observational, derived from his travels, historical study, and interactions with European converts rather than direct intellectual exchange with Islamic theologians.

Belloc’s personal contact with Muslims appears to have been limited to casual encounters during his extensive travels in the Mediterranean and Middle East, and conversations with European converts.  He explicitly noted in The Great Heresies (1938) that he had “known and talked to some half-dozen” educated European men who had converted to Islam, using these interactions to understand the faith’s appeal to those disillusioned with Christianity. However, he did not cite any debates, letters, or collaborations with established Muslim intellectuals or clerics.

Belloc viewed Islam as an “impregnable fortress” against Christian missionary efforts, noting that while Muslims might treat missionaries with courtesy, they were spiritually unmoved by them. 
 This perspective suggests a lack of deep theological dialogue; he saw the barrier between the faiths as absolute. His analysis focused on Islam’s resilience as a socio-political and spiritual force, rather than on engaging with its scholarly tradition. He praised the intellectual capability of individual Muslims—stating that an Egyptian or Syrian student was the equal of any European in philosophy or science—but this was a general observation of capability, not a record of personal academic exchange.

Hilaire Belloc viewed Islamic missionary efforts—specifically the conversion of Muslims to Christianity—as historically futile and spiritually impossible.  He famously described Islam as the “only spiritual force on earth which Catholicism has found an impregnable fortress,” noting that nearly 400 years of missionary work by great Catholic orders had “wholly failed” to convert individual Muslims. 

The “Unconvertible” Nature of Islam

Belloc argued that while Christian missionaries were often received with courtesy (and occasionally fierce attack), they were “never allowed to affect Islam.” He observed that:

  • Spiritual Immunity: Muslims spiritually despised Christian governments and remained unmoved by theological arguments. 
  • Internal Coherence: Unlike other heresies that faded, Islam retained a “closed” doctrinal system based on simplified truths (monotheism, divine justice) that satisfied its adherents completely, leaving no opening for Christian addition. 
  • One-Way Flow: Belloc noted that while Muslims never became Catholic, European eccentrics occasionally converted to Islam, drawn by its simplicity and perceived moral clarity compared to a secularizing West. 

Contrast with Islamic Expansion

In contrast to the failure of Christian missions within the Islamic world, Belloc acknowledged the historical success of Islam’s own expansion. He attributed this not to theological debate but to military conquest, political administration, and social incentives (such as the freeing of slaves and debtors).  He viewed Islam’s spread as a result of its vitality as a socio-political system rather than successful proselytization in the Christian sense. 

Hilaire Belloc defined the early spread of Islam as a synergistic process where military conquest created the political framework, but positive social incentives drove the actual conversion of populations.   He did not view these as mutually exclusive or purely negative forces; rather, he argued that the “sword” secured victory, while the promise of social justice secured the allegiance of the masses.

The Role of Military Conquest

Belloc explicitly stated that Islam’s sudden overwhelming success was primarily because “it won battles.” As a military historian, he acknowledged that the initial expansion into Syria, Egypt, North Africa, and Spain was achieved through superior military vitality and the “fighting material” of the early Muslim armies.  This military dominance broke the power of the Byzantine and Persian empires, removing the political barriers to Islam’s spread. However, Belloc noted that the conquerors were too few to govern by force alone, meaning military power established the rule but could not enforce religious conversion on a massive scale.

Social Incentives as the Driver of Conversion

Belloc characterized the subsequent conversion of subject peoples not as a result of coercion, but as a response to attractive social and economic advantages.  He described these incentives as positive liberations rather than negative pressures:

  • Freedom for Slaves and Debtors: Belloc emphasized that Islam offered immediate manumission to slaves and cancellation of debts for those who converted, a powerful draw in the stratified societies of the 7th century. 
  • Simplification of Law and Tax: He noted that the new regime offered “free justice” under simple laws and relief from the heavy, complex taxation of the previous imperial rulers. 
  • Social Equality: The doctrine that “all true believers are brothers” provided a sense of dignity and equality that was absent in the rigid class structures of the time. 

In Belloc’s analysis, the “sword” (as in the accusation of “conversion by the sword”) was the instrument of political conquest, but the social incentives were the “driving force” behind the religious victory.  He argued that people joined Islam “everywhere in great numbers” because they desired freedom from thraldom and debt, viewing the new faith as a vehicle for social and economic emancipation rather than merely a religion imposed by fear. 

References on Belloc’s views on Islam:

AI-generated answer. Please verify critical facts. “Generated with assistance from the Brave AI assistant, powered by Brave Search.”

Posted in Uncategorized | Tagged , , , , , , , , , | Leave a comment

How can America taxpayers constrain the enormous expense of NGO’s?

The one-third of the $40 trillion U.S. national debt has been identified.

The Federal Reserve CONFIRMS: The U.S. Congress has built the single largest racket empire on the planet:

U.S. NGOs have combined assets totaling $14.2 trillion of your tax money.

“India’s and Japan’s GDPs are each just over $4 trillion, Germany’s is $5 trillion, and together they total about $13.5 trillion. Guess what? The combined assets of U.S. NGOs equal $14.2 trillion of your tax money—and that of your children, grandchildren, and great-great-great-great-grandchildren.”

In other words, the root of all corruption—the racket—is the U.S. Congress. It has funneled as much as one-third of the U.S. national debt to the planet’s most profitable organizations: NGOs.

And you know what? As of 2026, the American taxpayer is paying roughly $1.2 trillion per year in interest on the racket.

Nancy Pelosi and Mitch McConnell oversaw approximately $30 trillion of the racket alone.

By the way, Democrats have spent approximately $1 trillion on illegal aliens over the last six years in an effort to overthrow the constitutional republic of the United States.

Giant hat tip to @Real_RobN over on X.

BUD’S QUESTIONS: How can a NGO be a Non-Governmental Organization if any, most or all of its funding comes from the government, i.e., taxpayers? Why are NGO’s allowed to influence government decisions through any branch of government when any, most or all of their funding comes from the government?

Here is a short video explanation:

https://twitter.com/Real_RobN/status/2091305412494864496/video/1

Carolyn Phippen is a conservative political activist and former candidate for the U.S. Senate from Utah, known for her strong advocacy of parental rights and constitutional conservatism.

Background and Early Life

Born in New York, Phippen moved to Utah to attend Brigham Young University (BYU), where she studied political science. She also served a mission for The Church of Jesus Christ of Latter-day Saints in the Prague Mission (then newly formed Czechoslovakia). After marrying, she completed her degree at the University of Utah.

Her upbringing and mission experience instilled in her a deep appreciation for American freedoms and a skepticism of government overreach.

Professional and Political Career

Before entering electoral politics, Phippen gained significant experience in policy and advocacy:

  • Staff Experience: She worked for Speaker Greg Hughes in the Utah House and later spent several years with U.S. Senator Mike Lee 1.
  • Consulting: She wrote for a national political consultant and ran a business coalition called Freedom Front, founded by local tech entrepreneurs to promote free markets and individual liberties 1.
  • Community Involvement: While raising her five sons for over 20 years, she was active in children’s organizations, including the Intermountain Suzuki String Institute, a private music program for at-risk youth, and a foster care review committee board 1.

Key Political Stances

Phippen’s platform centers on parental rights, limited government, and conservative social values, aligning closely with the interests I follow regarding Supreme Court rulings on family rights and school curricula.

  • Parental Rights: She is a vocal proponent of the “fundamental rights of parents” to make decisions regarding their children’s education, medical care, and moral upbringing. She has signed the “Parents Pledge,” promising to defend against government overreach in schools and oppose the teaching of critical race theory or gender ideology.
  • Abortion: Following the Supreme Court’s overturning of Roe v. Wade, Phippen argued that abortion policy should be decided at the state level rather than by a federal mandate, which is nearly identical to the Court’s position. She criticized proposals for a national 15-week ban, believing states should be free to set stricter limits.
  • Foreign Policy: She has taken a non-interventionist stance, stating the U.S. cannot afford to fund foreign aid for Ukraine or migrants, though she supports aid to Israel due to its strategic importance.
  • NGO Funding: In 2025, she gained attention for claiming that politically connected NGOs receive the vast majority of taxpayer money directed to nonprofits, a point echoed by Elon Musk.

Electoral History

  • 2023 U.S. Senate Race: Phippen ran for the Republican nomination to replace Mitt Romney but did not secure the nomination.
  • 2024/2025 Races: She has continued to run for office, including a campaign for Utah House District 46

“Biography summary generated with assistance from the Brave AI assistant, powered by Brave Search.”

Posted in Uncategorized | Tagged , , , , , , , | Leave a comment

Jeffrey Tucker Reveals The Insidious Reason For The Lockdowns

Tyler Durden's Photo

by Tyler Durden

Wednesday, Aug 19, 2026 – 06:25 AM

Jeffrey Tucker – founder and president of the Brownstone Institute, says top FDA and NIH officials told him that the purpose of the COVID-19 lockdowns were “to delay the onset of natural immunity… until after the shots were online.”

Tucker sat down for an hour-long conversation with Dr. Jessica Rose, where he says that ‘multiple sources’ who were involved in the response confirmed the bombshell revelation “without a shadow of a doubt.” 

As Vigilant Fox notes – 

The lockdowns that wiped out small businesses. The school closures that sent children’s reading scores back to 1971. The plexiglass, the masking, the stay-at-home orders. None of it was about keeping us safe. “It was exactly the opposite,” as Tucker put it.

Watch:

https://platform.twitter.com/embed/Tweet.html?dnt=false&embedId=twitter-widget-0&features=eyJ0ZndfdGltZWxpbmVfbGlzdCI6eyJidWNrZXQiOltdLCJ2ZXJzaW9uIjpudWxsfSwidGZ3X2ZvbGxvd2VyX2NvdW50X3N1bnNldCI6eyJidWNrZXQiOnRydWUsInZlcnNpb24iOm51bGx9LCJ0ZndfdHdlZXRfZWRpdF9iYWNrZW5kIjp7ImJ1Y2tldCI6Im9uIiwidmVyc2lvbiI6bnVsbH0sInRmd19yZWZzcmNfc2Vzc2lvbiI6eyJidWNrZXQiOiJvbiIsInZlcnNpb24iOm51bGx9LCJ0ZndfZm9zbnJfc29mdF9pbnRlcnZlbnRpb25zX2VuYWJsZWQiOnsiYnVja2V0Ijoib24iLCJ2ZXJzaW9uIjpudWxsfSwidGZ3X21peGVkX21lZGlhXzE1ODk3Ijp7ImJ1Y2tldCI6InRyZWF0bWVudCIsInZlcnNpb24iOm51bGx9LCJ0ZndfZXhwZXJpbWVudHNfY29va2llX2V4cGlyYXRpb24iOnsiYnVja2V0IjoxMjA5NjAwLCJ2ZXJzaW9uIjpudWxsfSwidGZ3X3Nob3dfYmlyZHdhdGNoX3Bpdm90c19lbmFibGVkIjp7ImJ1Y2tldCI6Im9uIiwidmVyc2lvbiI6bnVsbH0sInRmd19kdXBsaWNhdGVfc2NyaWJlc190b19zZXR0aW5ncyI6eyJidWNrZXQiOiJvbiIsInZlcnNpb24iOm51bGx9LCJ0ZndfdXNlX3Byb2ZpbGVfaW1hZ2Vfc2hhcGVfZW5hYmxlZCI6eyJidWNrZXQiOiJvbiIsInZlcnNpb24iOm51bGx9LCJ0ZndfdmlkZW9faGxzX2R5bmFtaWNfbWFuaWZlc3RzXzE1MDgyIjp7ImJ1Y2tldCI6InRydWVfYml0cmF0ZSIsInZlcnNpb24iOm51bGx9LCJ0ZndfbGVnYWN5X3RpbWVsaW5lX3N1bnNldCI6eyJidWNrZXQiOnRydWUsInZlcnNpb24iOm51bGx9LCJ0ZndfdHdlZXRfZWRpdF9mcm9udGVuZCI6eyJidWNrZXQiOiJvbiIsInZlcnNpb24iOm51bGx9fQ%3D%3D&frame=false&hideCard=false&hideThread=false&id=2087254056796352654&lang=en&maxWidth=560px&origin=https%3A%2F%2Fwww.zerohedge.com%2Fpolitical%2Fjeffrey-tucker-reveals-insidious-reason-lockdowns&sessionId=63d5b0d4214e7253b5982d68e5e47c36c1d650ff&siteScreenName=zerohedge&theme=light&widgetsVersion=6a3ad42b224df%3A1778106238597&width=550px

TUCKER: “We all have what we consider to be the most shocking feature of the COVID response. But for me, I still can’t get over the fact that I was told by top FDA, NIH officials that a major reason for social distancing, lockdowns, masking, Plexiglas, stay-at-home orders, and everything else was to delay the onset of natural immunity, to delay rising seroprevalence levels, to delay endemicity until after the shots were online.

“So, it wasn’t just that all these tactics, these sort of social engineering tactics, were designed to keep us [safe]. Well, no, it was exactly the opposite. It was to keep us from gaining natural capacity to resist the virus.

“So that they could wait until the injection came along. So the injection could be deployed and experimented upon us and, and thereby get all the credit for having solved the issue.

“That sounds like a wild conspiracy theory, but that’s what they meant by ‘flatten the curve.’ Flatten the curve meant to prolong the pain, delay the solution. And it sounds crazy until you hear it from people who were there on the ground, in the agencies, in the companies, watching all this unfold.

“And multiple sources have confirmed this without a shadow of doubt in their mind that was the real purpose of the school closures, the business shutdowns, the stay-at-home orders, the travel restrictions, and everything: to delay the point at which we would have solved, essentially solved, the problem through natural exposure and immune upgrades.”

h/t Vigilant Fox – give him a follow!

https://www.zerohedge.com/political/jeffrey-tucker-reveals-insidious-reason-lockdowns

Posted in Uncategorized | Leave a comment

The end of the climate change obsession, by Electroverse  @Electroversenet on X

Electroverse

A Google Scholar search for the phrase “climate change” reveals studies exploded from the years 2000 to 2020, peaking at 900,000, but extrapolations for 2026 now show just 175,000 – an 80% collapse. 

A Google Scholar search for the phrase “climate change” reveals studies exploded from the years 2000 to 2020, peaking at 900,000, but extrapolations for 2026 now show just 175,000 – an 80% collapse. 

A Google Scholar search for the phrase “climate change” reveals studies exploded from the years 2000 to 2020, peaking at 900,000, but extrapolations for 2026 now show just 175,000 – an 80% collapse.

Climatologist Judith Curry argues the boom was never organic.

“This is not a natural scientific consensus that has emerged over a long time,” she says. “It’s a manufactured consensus of scientists at the request of policymakers.”

Curry says funding, promotion and professional acceptance rewarded researchers who stayed inside the narrative, while dissent carried a price.

Curry says she paid it herself: “I was essentially unhirable academically… they pretty much finished me off.”

Over time, more and more social, economic and environmental problems were folded under the same climate umbrella.

This led to policy where subsidies, carbon taxes and renewable mandates worked together to restructure Western energy systems (and economies). And so follows Curry’s warning: “The biggest climate risk right now is the so-called transition risk.”

The climate machine has not disappeared, not entirely, but the academic frenzy paid to feed it looks to have peaked. This is likely because the establishment now has a new obsession: AI, which, amusingly, demands vast quantities of cheap, reliable 24-7 electricity – things wind and solar cannot provide.

So something has to give, and that something looks to be ‘climate alarm’.

https://twitter.com/Electroversenet/status/2090091426554012157/video/1

Posted in Uncategorized | Tagged , , , , , | Leave a comment

Democratic socialism?

Wall Street Apes @WallStreetApes

, 2026

, 2026

This PERFECTLY explains the Capitalism vs Socialism argument for America “So now, Colombia rejected a socialist. Peru rejected a socialist. El Salvador, Chile, Honduras, Ecuador, Bolivia, Argentina all rejected Marxist or socialist leadership. And Venezuela was destroyed by socialism. Latin Americans are rejecting socialism after having tried it. So why are Americans accepting socialism, having never tried it? Well, partially because most Americans don’t know what socialism is It’s not healthcare for all or affordable housing. Socialism isn’t a synonym for all the things I want, but I’m not getting in my capitalist country. It’s not a vibe. It’s an economic system characterized by collective or governmental ownership of the means of production. Means of production meaning infrastructure used to produce goods and services like factories, farms, and companies. Capitalism also isn’t a vibe. It’s not billionaires and corporations controlling politics. It’s not a synonym for all the things I hate about my country. It’s an economic system characterized by private or corporate ownership of capital goods, AKA the means of production. Now, just like Mac versus Windows, there are different versions of capitalism and socialism. Finland, Norway, Denmark, and Sweden are less capitalistic than America, but they are still capitalist. Although they have a few exceptions to the rule, private companies own the means of production, not the government in those countries. Now, you might like certain programs that socialism promises, like universal healthcare, but those programs aren’t tied to a specific operating system. You can run Photoshop on Mac or Windows, just like you can have universal healthcare in socialism or capitalism. But it seems we as a people keep getting more confused about what socialism is. In 1949, 34% of Americans correctly identified socialism as government ownership of the economy. By 2018, only 17% did, and I suspect it’s even worse now. American politicians are confused, too. In 2015, Denmark’s prime minister had to correct Bernie Sanders and say, “Denmark is far from a socialist planned economy. Denmark is a market economy.” Zoran Mamdani is a democratic socialist. Democratic socialism is a version of socialism. Now, you could argue that socialism just hasn’t been done right yet. And when every socialist experiment at the national level in the 20th century failed, and every experiment in the 21st century is failing, maybe the problem isn’t that socialism hasn’t worked in practice, it, that it almost certainly can’t work in principle. And maybe the assertion that this time will be different isn’t optimism, it’s actually just unfalsifiability, where a theory cannot ever be contradicted by actual evidence. We have bugs in this version of capitalism that need to be fixed, principally that there is too much money in politics, that billions of dollars speak louder than millions of voices. And you know what? The socialists might create healthy pressure to fix those bugs. That’s good, but that’s different than changing the whole operating system. Sometimes the cure is worse than the disease. Because when there’s never been a successful socialist country in history, and the countries who have actually experimented with it are abandoning it, the results start to speak for themselves. And lately, they’re speaking Spanish.”

And just so we’re crystal clear, here are the stated goals of the Democratic Socialists of America in America

-Abolish the US Senate

– Replace the Presidency and Supreme Court

– Abolish the Electoral College

• Abolish police and the prison system

• Abolish ICE, grant amnesty to all immigrants and end visa restrictions

• Public ownership of the largest corporations

– Defund the US military

– End economic sanctions on Iran

– Government owned social housing

https://twitter.com/WallStreetApes/status/2088283252238991835/video/1

Posted in Uncategorized | Tagged , , , , | Leave a comment

What’s wrong with public education?

Handre @Handre

2026 on X

USA 2026 The teachers’ union does not exist to educate your children. It exists to extract wages, block accountability, and eliminate competition, and it does this through the oldest trick in the statist playbook: capturing the regulatory apparatus that controls entry into the market. School vouchers threaten this arrangement directly. When a family in Milwaukee receives a $8,000 voucher and walks it across the street to a private school, the public school loses that funding. The union loses dues from teachers that the school no longer needs to employ. You can see exactly why the National Education Association (NEA), alongside the American Federation of Teachers (AFT), has spent part of a combined $669.3 million since 2015 opposing school choice. The public school system is a state-enforced cartel. Funding flows in through compulsory taxation regardless of performance. Families cannot easily exit without paying twice, once in taxes and again in private tuition. This structure is intended. Monopolies do not emerge from free exchange; they require coercion to sustain themselves. Free market economists have long pointed out that competition disciplines producers by giving consumers exit options. Remove the exit option, and producers serve themselves. American public schools spend an average of $17,000 per pupil annually while countries like South Korea and Finland achieve superior results at lower costs in more competitive environments. The numbers do not flatter the monopoly. What the union calls “protecting public education” is protecting a captive market. Children in that market have no leverage, no exit, and no recourse when administrators fail them for the ninth consecutive year. The state compels your attendance, compels your funding, then tells you the resulting mediocrity is a public good worth defending.

Posted in Uncategorized | Leave a comment
